Tranexamic Acid Serum: What the Trials Used, and How to Choose One
Tranexamic acid has become the go-to gentle ingredient for stubborn dark patches. Here is what the evidence actually tested, how long it takes, and what to look for on the label
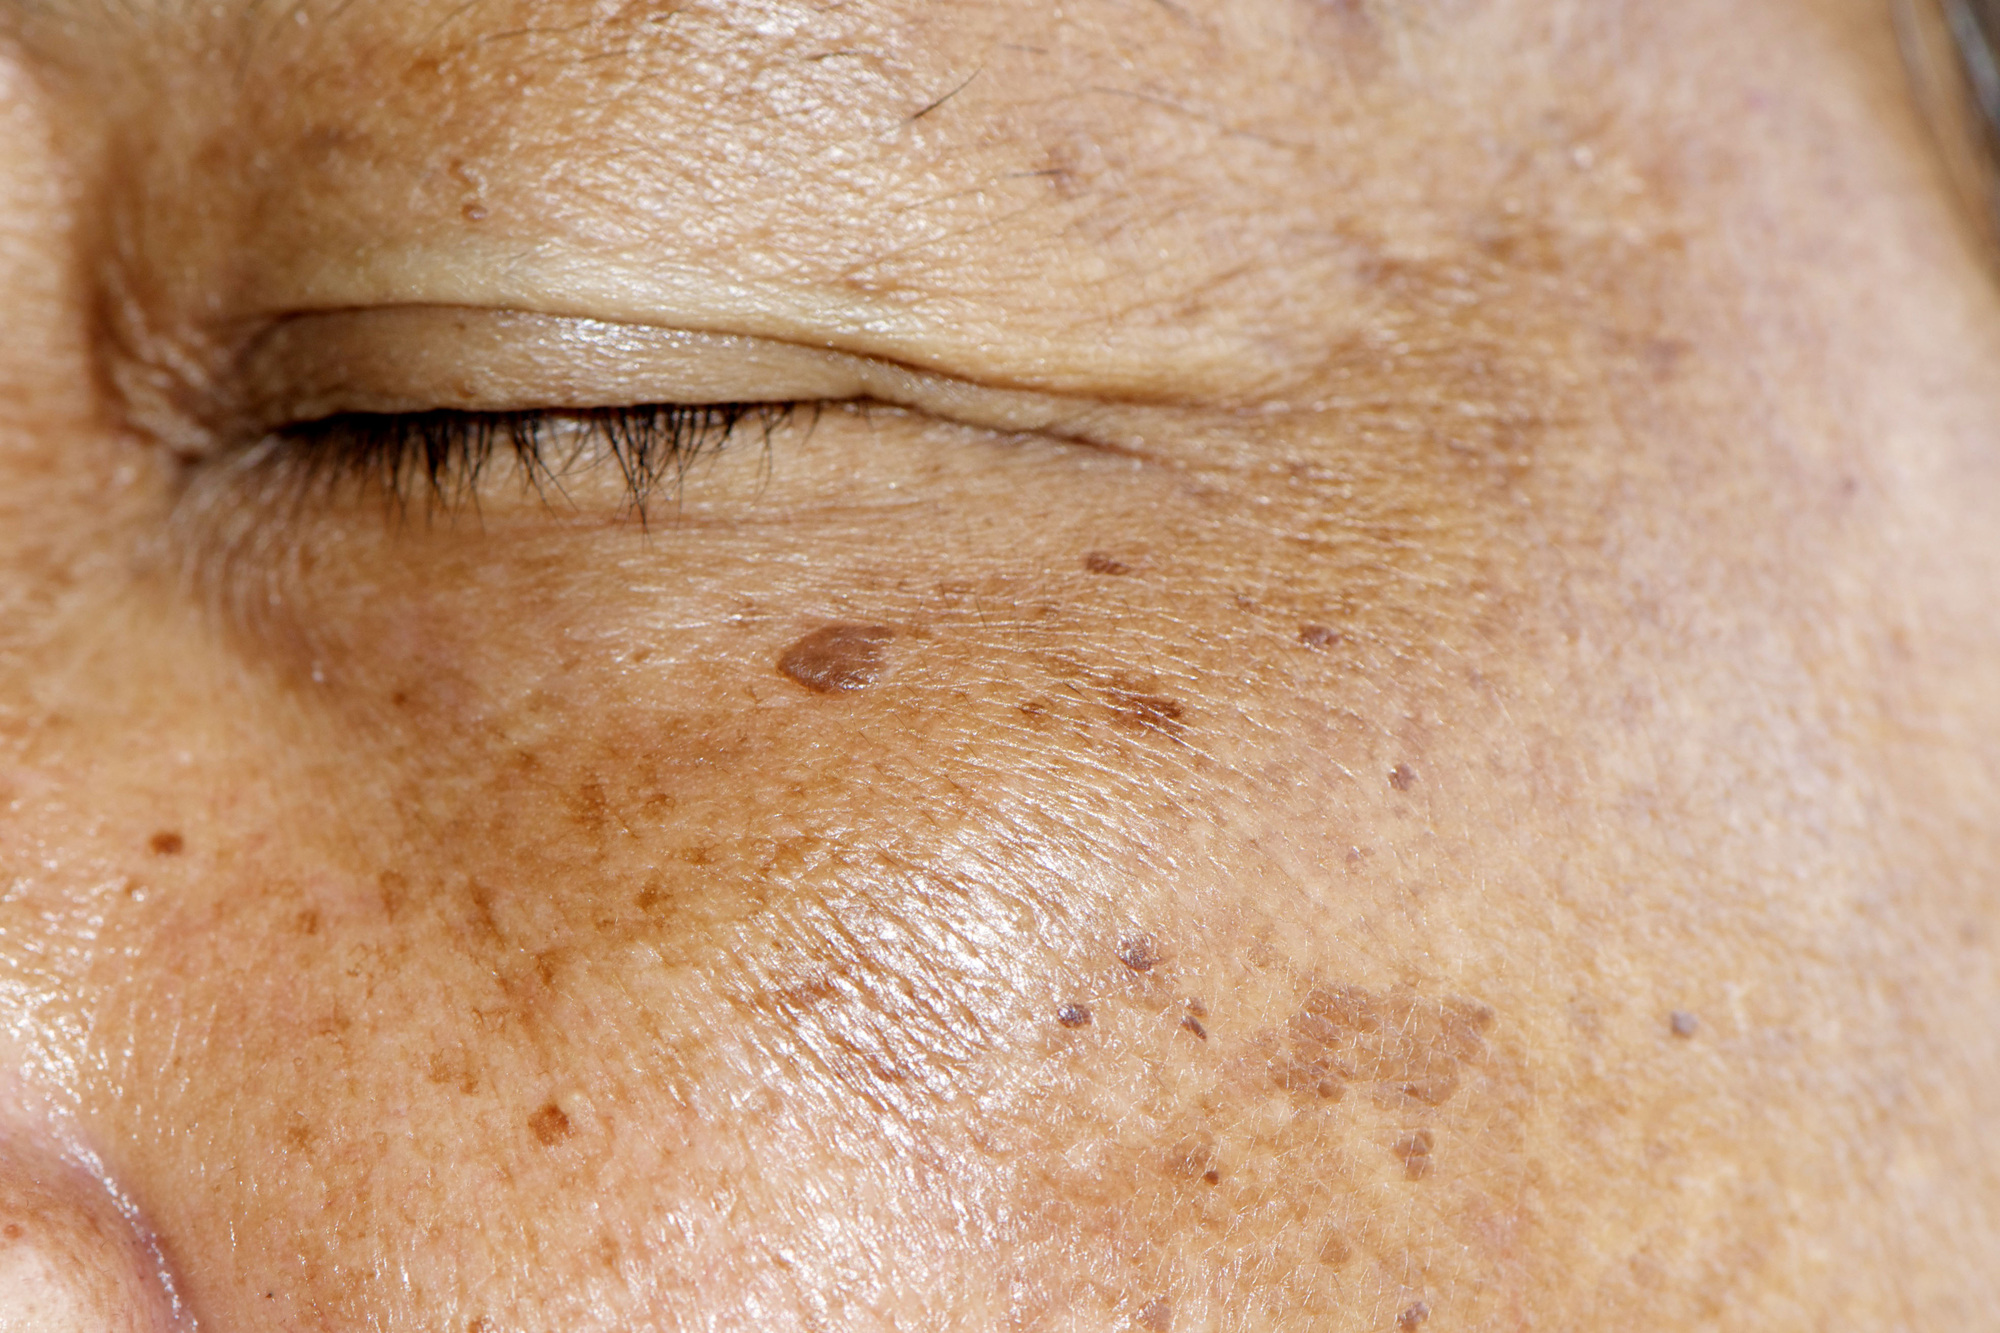
Few skincare ingredients have gone from obscure to everywhere as quickly as tranexamic acid. A few years ago it was mostly known as a hospital drug that helps blood clot. Today a tranexamic acid serum sits on almost every shelf that sells dark spot treatments, usually with a promise of fading melasma and stubborn patches without the irritation of stronger lighteners.
Some of that promise is real. Topical tranexamic acid has been tested head to head against hydroquinone, the long-standing dermatology benchmark, and it holds up well, especially on comfort. Still, the trials tell a more specific story than the marketing does, and that story is what should guide the serum you buy.
How tranexamic acid fades pigment
Most brightening ingredients work on the melanocyte, the cell that makes pigment. Tranexamic acid works one step earlier. When UV light hits skin, keratinocytes release an enzyme called plasmin, which sets off a chain of signals telling melanocytes to make more melanin. Tranexamic acid blocks that plasmin activity.
In an early study, applying tranexamic acid to skin before UV exposure prevented the tanning response that would normally follow [1]. Later work in people with melasma added a second mechanism. After 12 weeks of a 2% topical tranexamic acid, biopsies showed significantly less pigment in the epidermis, lower levels of endothelin-1 (a signal that stimulates melanocytes), and a trend toward fewer small blood vessels [2]. That matters because the blood supply in melasma skin appears to feed the signals that keep pigment coming back.
That distinction explains both its strengths and its limits. It is excellent at stopping pigment from rebuilding, which is why it suits recurring problems such as melasma and sun-triggered patches. It is slower at removing a spot that is already fully formed. For the ingredient’s wider background, see our guide to tranexamic acid for dark spots.
Every trial ran about 12 weeks, so a serum you abandon after three weeks has not had a fair test.
What the clinical trials actually tested
The label percentage on your serum is worth comparing with what researchers used:
- 2% tranexamic acid, applied to the whole face for 12 weeks, improved melasma scores in 22 of 23 participants [2].
- 3% tranexamic acid was compared with a hydroquinone and dexamethasone solution on opposite halves of the same face in 50 women for 12 weeks. Both sides improved to a similar degree, and the tranexamic acid side had significantly fewer side effects [3].
- 5% tranexamic acid solution was compared with 3% hydroquinone cream in 100 patients over 12 weeks. Both cut melasma scores by about 27%, and patient satisfaction was higher with tranexamic acid because of its milder side effects [4].
Three things stand out. The studied range is roughly 2% to 5%, so a serum in that band is in evidence-backed territory. Every trial ran about 12 weeks, so a serum you abandon after three weeks has not had a fair test. And the headline advantage over hydroquinone was comfort, not superior fading.
Oral tranexamic acid, which dermatologists sometimes prescribe for severe melasma, produces faster and larger improvements, but it is a prescription drug that affects blood clotting and is not appropriate for everyone [5]. A topical serum trades some speed for a much better safety profile.
Choosing a tranexamic acid serum
Use the trial data as your checklist:
- A stated percentage between 2% and 5%. Formulas that list tranexamic acid near the end of the ingredients without a number are unlikely to reach studied levels.
- A water-based vehicle. Tranexamic acid dissolves in water, not oil. It belongs in a serum, essence or gel rather than a facial oil.
- Sensible partners. Niacinamide, which blocks pigment transfer to skin cells, and gentle hydrators such as glycerin work alongside it. Our guide to the best brightening serums explains how different mechanisms combine.
- Fragrance-free. Melasma skin tends to be reactive, and inflammation can itself trigger new pigment.
- Realistic claims. A serum promising results in seven days is selling hope, not the 12-week timelines in the literature.
The studied range is roughly 2% to 5%, so a serum in that band is in evidence-backed territory.
How to use it for the best results
Tranexamic acid is one of the easiest actives to fit into a routine. It is not an acid in the exfoliating sense, it does not make skin more sun-sensitive, and it rarely stings. The trials used it once or twice daily, so morning and night on clean skin, before moisturizer, is a reasonable default.
The single biggest factor in whether it works is what you do in daylight. Visible light and UV both drive melasma, and a few unprotected hours can undo weeks of progress. A broad-spectrum sunscreen every morning, ideally a tinted formula with iron oxides for melasma-prone skin, is part of the treatment rather than an optional extra. Our guide to sunscreen for hyperpigmentation covers what to look for.
Expect a gradual change. In the trials, scores were checked every four weeks and improvement built steadily toward the 12-week mark, so judge your serum at three months, not three weeks. Melasma is chronic, so many people keep a tranexamic acid serum in their routine long term to stop it returning. Our guide to melasma treatment covers the options when a serum alone is not enough.
Where tranexamic acid stops, and retinol starts
Tranexamic acid is a brake. It slows the production of new pigment, but it does little to clear the pigment already sitting in the upper layers of skin. That clearing depends on cell turnover: the steady replacement of surface cells that carries old pigment up and out.
This is where retinoids earn their place. In a 40-week vehicle-controlled trial, 68% of women with melasma using prescription 0.1% tretinoin were rated improved or much improved, compared with 5% on the vehicle cream, and epidermal pigment fell by 36% [6]. Retinoids speed turnover and help clear pigment from the epidermis, which is the half of the problem tranexamic acid does not address. The same trial also showed the trade-off: redness and peeling affected 88% of tretinoin users, and irritated skin is exactly what melasma-prone skin should avoid.
A pairing that respects sensitive skin
The practical routine is simple. Use a tranexamic acid serum in the morning under sunscreen, and at night follow it with a gentle retinol on clean skin.
That is where Nanoretinol fits. It carries stabilized 0.2% retinol inside biomimetic lipid nanoparticles that the skin recognises as its own, so the retinol reaches skin cells without breaking down the barrier the way conventional formulations can. In North Biomedical’s study summary, Nanoretinol was 232% more effective in collagen recovery than conventional retinol and produced a 61% increase in firmness after 56 days, with side effects that were minimal and milder than those of conventional retinol [7]. For skin that reacts to irritation with more pigment, a gentler retinol is not a luxury; it is what makes a consistent routine possible.
Tranexamic acid quiets the signal, retinol clears the backlog, and sunscreen stops the cycle starting again. Give the combination 12 weeks before you judge it.
References
- Maeda K, Naganuma M. “Topical trans-4-aminomethylcyclohexanecarboxylic acid prevents ultraviolet radiation-induced pigmentation.” Journal of Photochemistry and Photobiology B: Biology. 1998;47(2-3):136-141. PubMed: 10093913
- Kim SJ, Park JY, Shibata T, Fujiwara R, Kang HY. “Efficacy and possible mechanisms of topical tranexamic acid in melasma.” Clinical and Experimental Dermatology. 2016;41(5):480-485. doi:10.1111/ced.12835
- Ebrahimi B, Naeini FF. “Topical tranexamic acid as a promising treatment for melasma.” Journal of Research in Medical Sciences. 2014;19(8):753-757. PubMed: 25422661
- Janney MS, Subramaniyan R, Dabas R, Lal S, Das NM, Godara SK. “A Randomized Controlled Study Comparing the Efficacy of Topical 5% Tranexamic Acid Solution versus 3% Hydroquinone Cream in Melasma.” Journal of Cutaneous and Aesthetic Surgery. 2019;12(1):63-67. doi:10.4103/JCAS.JCAS_40_18
- Bala HR, Lee S, Wong C, Pandya AG, Rodrigues M. “Oral Tranexamic Acid for the Treatment of Melasma: A Review.” Dermatologic Surgery. 2018;44(6):814-825. doi:10.1097/DSS.0000000000001518
- Griffiths CE, Finkel LJ, Ditre CM, Hamilton TA, Ellis CN, Voorhees JJ. “Topical tretinoin (retinoic acid) improves melasma. A vehicle-controlled, clinical trial.” British Journal of Dermatology. 1993;129(4):415-421. doi:10.1111/j.1365-2133.1993.tb03169.x
- North Biomedical LLC. “Nanoretinol vs. Conventional Retinol: Efficacy in Collagen and Elastin Recovery.” Clinical Study Summary, 2024. Study summary